 Ghatkopar (East), Mumbai)


Table Of Content
Patient Resources
Billing, Insurances & Estimates
Admission & Discharge
Visitors’ Rules
International Patients
Hospital Facilities
Health Packges

For Appointment/Query
1800-268-4000

Search or
Find Specialist
What Is CRS HIPEC? How It Works and Who May Be a Candidate
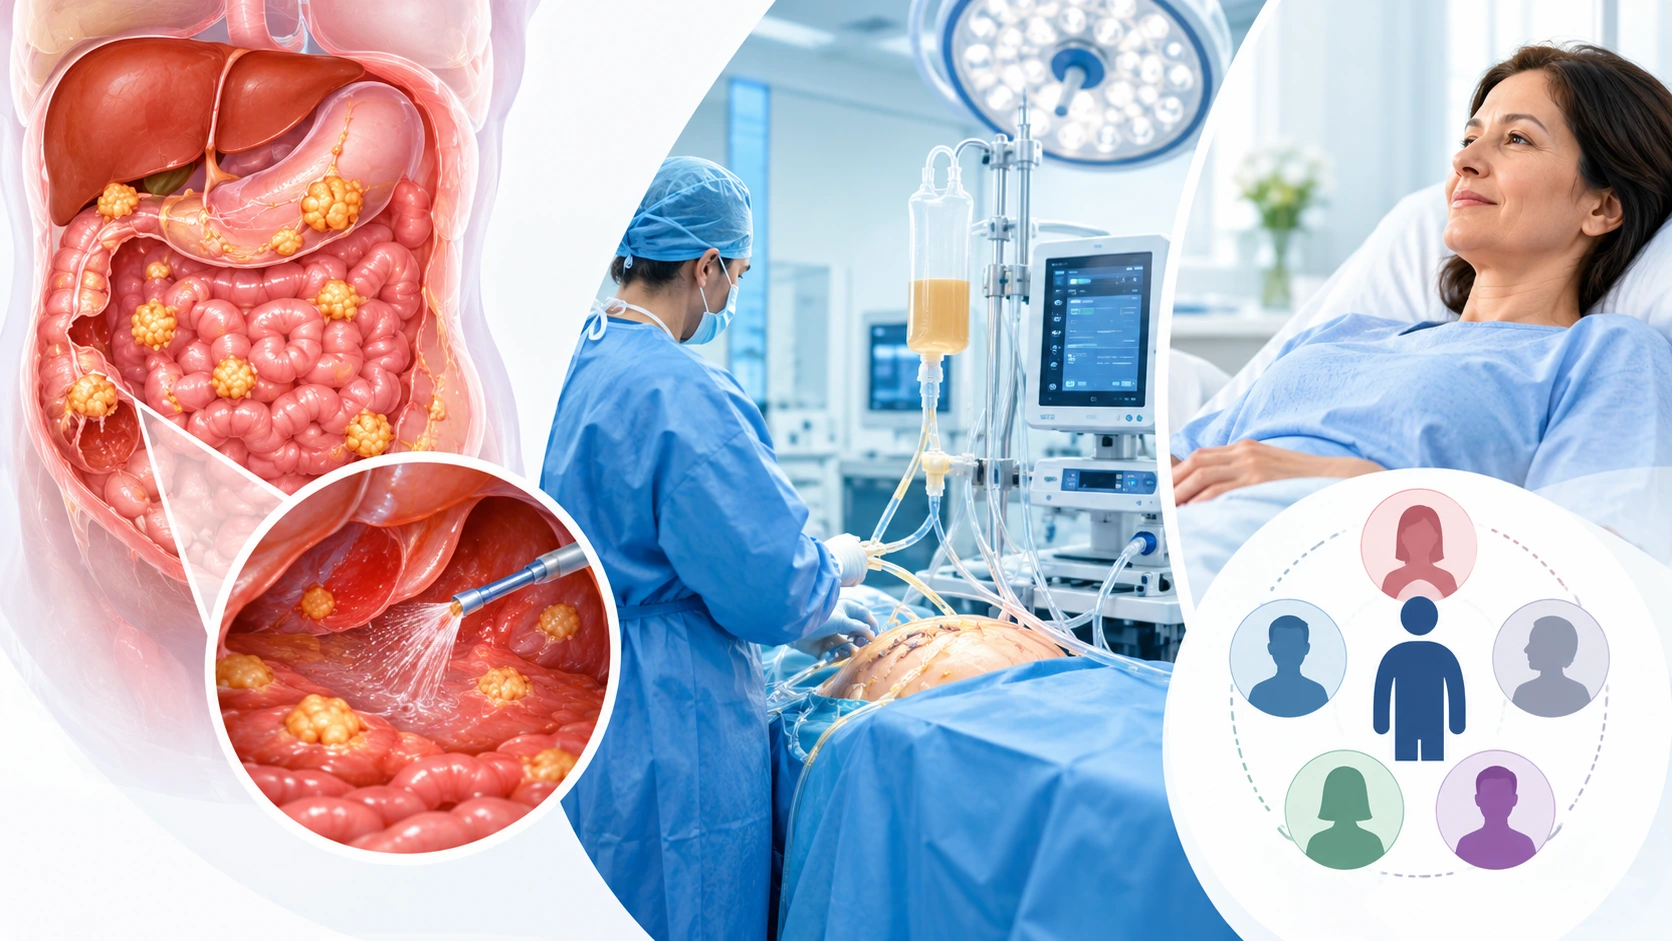
CRS HIPEC combines two treatments in one operation. First, a surgeon removes all visible cancer from the abdomen. This is cytoreductive surgery (CRS). Then heated chemotherapy is circulated inside the abdominal cavity to reach cancer cells the surgeon cannot see. This is hyperthermic intraperitoneal chemotherapy (HIPEC).
It is used only for selected people whose cancer has spread to the lining of the abdomen. This guide explains how it works, which cancers it is used for, and who may be a candidate.
Quick Answer
- CRS: surgery to remove all visible tumour in the abdomen.
- HIPEC: heated chemotherapy delivered directly into the abdomen during the same operation.
- Used for: selected cancers that have spread to the peritoneum, such as appendix, colorectal and ovarian cancer.
- Not for everyone: it is major surgery, and it suits only people whose disease can be removed completely and who are fit enough.

Reviewed By
Shree Hospitals Multi-Speciality Care
Treatment:
Head & Neck Cancer Surgery
Key takeaways
- CRS HIPEC is not a cure for every patient. Penn Medicine says it is not a cure but has been shown to extend life and reduce recurrence in some patients.
- Evidence differs by cancer type. Ask what the evidence is for yours.
- Specialist teams decide eligibility using scans, a scoring system and your overall health.
What does CRS HIPEC stand for?
The UK's National Institute for Health and Care Excellence (NICE) describes the first part, cytoreductive surgery, as removing all the visible cancer. The second part fills the abdominal cavity with heated chemotherapy fluid to reach any cancer cells the surgery may have missed.
- Cytoreductive: cytoreduction means reducing the tumour burden.
- Hyperthermic: heated above normal body temperature.
- Intraperitoneal: inside the abdominal cavity (the peritoneum is its lining).
Why is it used for peritoneal cancer?
When cancer spreads to the lining of the abdomen it is called peritoneal metastasis or peritoneal carcinomatosis. Standard chemotherapy travels through the bloodstream, and it may not reach these surface tumours well. CRS HIPEC treats the abdomen directly.
The idea is that, in selected patients, the disease stays within the abdomen. One report on colorectal cancer notes that surgery removes the visible tumour and HIPEC targets the microscopic disease. That is the reason for the treatment, not a guarantee that it works for every person.
How does CRS HIPEC work, step by step?
- Assessment: scans, blood tests and a fitness check. Your team may suggest an Enhanced Recovery After Surgery (ERAS) plan (Altru Health ).
- Exploration: the surgeon examines the abdomen, scores the disease and decides whether complete removal is possible. Sometimes it is not, and the plan changes during surgery.
- Cytoreductive surgery: the surgeon removes visible tumour and affected tissue. This may include parts of the bowel, peritoneum or other organs, depending on spread.
- HIPEC: the chemotherapy is warmed above body temperature. Sinai Health explains that this helps the drug reach tissue lined with cancer cells. The drug is circulated through the abdomen for a set time, then drained.
- Reconstruction: the surgeon reconnects the bowel where needed, and sometimes creates a temporary or permanent stoma.
How long does it take? Hospital sources give wide ranges. Cleveland Clinic Abu Dhabi says about 5 to 10 hours, and Altru Health says 6 to 12 hours, depending on how much cancer is found.
Some care teams use open surgery. Your surgeon will explain which approach suits you. Read about our GI cancer surgery and gynecologic cancer surgery services.
How is HIPEC different from regular chemotherapy?
| Regular (systemic) chemotherapy | HIPEC | |
| How it is given | Through a vein or by mouth | Directly into the abdomen |
| When | Over weeks or months | Once, during surgery |
| Where it acts | Whole body | Mainly inside the abdomen |
| Heated? | No | Yes |
| Needs surgery? | No | Yes, always with CRS |
Many patients still need systemic chemotherapy before or after surgery. HIPEC does not replace it.
Who may be a candidate for CRS HIPEC?
No single rule decides this. A multidisciplinary team looks at the cancer type, how much disease there is, how fit you are, and whether complete removal is realistic.
|
Factor |
Why it matters |
|
Cancer type |
Evidence and results differ for each cancer |
|
Extent of disease (PCI score) |
Predicts whether all visible tumour can be removed |
|
Disease confined to the abdomen |
Spread to distant organs may rule it out |
|
Overall fitness |
You must tolerate a long, major operation |
|
Response to earlier treatment |
Helps the team judge the cancer's behaviour |
What is the PCI score?
The Peritoneal Cancer Index (PCI) scores the extent of disease across 13 abdominal regions. It ranges from 0 to 39. A lower score means less disease and a better chance of complete removal. There is no universal cut-off. It varies by cancer type and centre.
What is the CC score?
The completeness of cytoreduction (CC) score is recorded after surgery. A CC-0 means no visible tumour is left. CC-1 means only very small deposits remain (under 2.5 mm). The same source says CC-0 and CC-1 are the goal, and CC-2 and CC-3 results are not currently advised for colorectal cancer (PMC review).
Example of selection criteria used in a trial
The French PRODIGE 7 trial enrolled people aged 18 to 70 with a good performance status, a PCI of 25 or less, and enough organ function to receive systemic chemotherapy. Real-world selection depends on your team and cancer type.
Who may not be a candidate?
HIPEC may not be recommendedif cancer has spread to distant organs or if a person cannot tolerate surgery. It may also not be suitable when too much disease is present to remove completely.
Which cancers are treated with CRS HIPEC?
| Cancer | What to know |
| Appendix cancer, pseudomyxoma peritonei | Often considered at specialist centres |
| Colorectal | PRODIGE 7 found no extra survival benefit from adding oxaliplatin-based HIPEC to surgery alone; surgery to remove all visible disease remains central |
| Ovarian | One randomised trial reported longer median survival with HIPEC at surgery (about 46 vs 34 months) |
| Gastric (stomach) | Considered experimental, within clinical studies at high-volume centres |
| Peritoneal mesothelioma | Considered at specialist centres |
| Endometrial | One study found no survival difference between CRS HIPEC and CRS alone |
Sources: Lancet Oncology (PRODIGE 7); American College of Surgeons Bulletin; gastric review; endometrial study.
Trial results apply to the group studied, and the drug, timing and patient selection all matter. Ask your surgeon how the evidence applies to your cancer. Read about colon cancer, rectal cancer, ovarian cancer and stomach cancer care. A separate guide will cover survival evidence cancer by cancer:HIPEC by cancer type: what the evidence says.
What are the risks of CRS HIPEC?
It is a complex procedure with serious risks. Altru Health lists them, and Penn Medicine names infection and bleeding among them. The PRODIGE 7 authors also reported more frequent late complications when HIPEC was added.
- Infection and bleeding
- Bowel leak or slow bowel recovery
- Low blood counts or kidney effects from chemotherapy
- Blood clots
- Need for a stoma in some cases
- Cancer may still return, in the abdomen or elsewhere
A specialist team and intensive care support matter. Learn about our post-surgical ICU care.
What is recovery like?
Recovery takes time. In a Swedish audit of 76 patients, eating, bowel function and walking usually returned between 7 and 11 days after surgery, nausea lasted up to 13 days, and many had sleep and emotional difficulties in the first three weeks. Your own course will differ. A detailed week-by-week guide is in HIPEC recovery guide.
Questions to ask your surgeon
- Is CRS HIPEC an option for my cancer type and spread?
- What is my PCI score, and how likely is complete removal?
- What does the evidence say for my cancer?
- How often does your team perform this operation?
- What are the main risks for someone like me?
- Will I need a stoma or ICU care?
- Do I need chemotherapy before or after?
- Can I get a second opinion?
When should you see a doctor?
See a cancer specialist if you have been told your cancer has spread to the abdominal lining and you want to know your options. Get urgent care if you have severe abdominal pain, fever, repeated vomiting, or a swollen painful abdomen.
CRS HIPEC care in Mumbai
Choosing a centre matters, because this is a specialised operation. Shree Hospitals, Ghatkopar East, lists HIPEC among its specialty clinics. A consultation can review your scans and explain whether you are a candidate, including when it is not. Bring your scan reports, biopsy reports and a list of questions, then book a consultation or find a specialist. For costs and insurance, see HIPEC surgery in Mumbai: costs, insurance and questions.
Frequently Asked Question
Is CRS HIPEC a cure?
Not for everyone. It is described as a treatment that can extend life and reduce recurrence in some patients, not a guaranteed cure.
Is HIPEC the same as chemotherapy?
It is chemotherapy, but given heated and directly into the abdomen during surgery. Many people also need standard chemotherapy.
Why is the chemotherapy heated?
Warming it helps the drug reach tissue lined with cancer cells
Can HIPEC be done without surgery?
No. It is given with cytoreductive surgery. Other intraperitoneal methods exist but are different treatments.
What is a good PCI score for HIPEC?
There is no universal number. It depends on the cancer type and centre. Lower scores generally mean less disease.
Can the surgery be cancelled during the operation?
Yes. If the surgeon finds more disease than expected and cannot remove it completely, the plan may change.
Is HIPEC available for stage 4 cancer?
Sometimes, if the spread is confined to the abdomen. Spread to distant organs may rule it out.
How long is the hospital stay?
It varies with the extent of surgery and recovery. Ask your team for an estimate for your case.
Will I need a stoma?
Some people do, depending on the bowel work needed.